


India’s Sickle Cell Fight Faces New Challenge: Ensuring Continuous Care After Screening
Experts say identifying patients is only the first step, with regular treatment, medicine availability, counselling and follow-up needed to improve outcomes.
NEW DELHI, Sept 30: India’s national effort to tackle sickle cell disease is entering a crucial phase as health experts call for greater attention to treatment and long-term follow up after screening.
India has screened more than seven crore people for sickle cell disease and identified around 2.5 lakh patients along with nearly 20 lakh carriers, according to healthcare sector reporting published on September 30. The figures represent a major expansion of screening under the country’s Sickle Cell Anaemia Elimination Mission, but experts have cautioned that identifying affected individuals must be followed by sustained care.
The issue was discussed at a national roundtable involving clinicians, scientists, government representatives and patient advocacy groups. Participants highlighted gaps that can arise after diagnosis, including delayed communication of test results, patients dropping out of care, shortages of medicines and limited access to advanced treatment options.
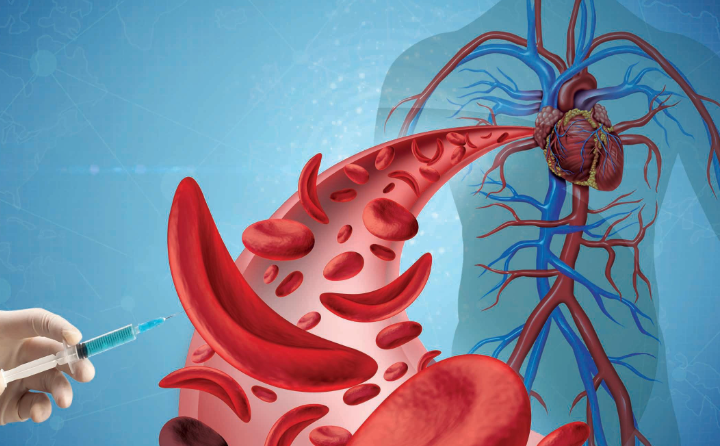
Sickle cell disease is an inherited blood disorder in which red blood cells can become rigid and take on an abnormal shape. The condition can interfere with blood flow and lead to episodes of severe pain, anaemia and other complications affecting different organs.
Because the disease requires continuing management, screening alone cannot provide the full benefit of a national elimination programme. People who are identified as having the condition need access to appropriate medical supervision, medicines, laboratory monitoring and counselling.
The government’s Sickle Cell Anaemia Elimination Mission was launched in 2023 with a target of screening seven crore people in affected districts. The official Swasth Bharat dashboard currently lists more than 7.1 crore beneficiaries screened under the sickle cell programme.
The scale of screening has created a large pool of individuals who need clear information about their results and access to appropriate services. Experts participating in the recent discussion therefore called for better systems to connect screening programmes with treatment facilities.
One proposed approach is the use of unique patient identifiers that would allow individuals diagnosed through screening to remain connected with healthcare services. Such systems could help doctors and health workers track whether patients are receiving medicines and attending follow-up appointments.
Telemedicine was also highlighted as a potential tool, particularly for people living in remote areas where specialist services may not be readily available.
Access to essential medicines remains another important consideration. Hydroxyurea is among the medicines used in the management of sickle cell disease, while patients with more severe complications may require additional interventions, including blood transfusions.
The national programme’s long-term success therefore depends not only on finding affected people but also on ensuring that healthcare facilities can respond to their needs after diagnosis.
The government has already identified screening and counselling as major components of the national mission. Earlier health ministry guidance has also stressed the need to address diagnostic supply chains, ensure availability of essential medicines and strengthen counselling services.
Experts say counselling is particularly important because sickle cell disease has implications not only for individual health but also for families. People identified as carriers may need information about their carrier status and appropriate genetic counselling.
Early identification can help families and healthcare providers make informed decisions and allow affected children to begin appropriate care sooner.
Children diagnosed with sickle cell disease require particularly careful monitoring because complications can begin early in life. Regular medical assessment can help identify problems before they become severe.
For patients with established disease, continuing treatment is important because sickle cell complications can occur repeatedly over a lifetime. Interruptions in medication or follow-up can leave patients vulnerable to preventable health problems.
Experts at the national roundtable also pointed to the need for stronger participation by frontline health workers. ASHA workers and other community-based personnel can play an important role in helping families understand test results, encouraging follow-up visits and identifying patients who have stopped receiving care.
Village-level medicine availability was among the recommendations discussed as a way to reduce interruptions in treatment, especially for patients living far from district hospitals.
The challenge is particularly significant in communities where healthcare access is affected by distance, transport costs, limited awareness or shortages of specialist services.
Advanced treatment presents another layer of difficulty. Haematopoietic stem cell transplantation can offer a potential cure for selected patients, but access remains limited and outcomes depend on factors such as timely referral, donor availability and the patient’s clinical condition.
Experts have also discussed gene therapy as an emerging possibility. However, they have emphasised that advanced technologies cannot substitute for basic healthcare systems capable of diagnosis, regular monitoring, medicines and supportive care.
The government’s stated objective is to eliminate sickle cell disease as a public health problem by 2047. Achieving that goal will require the screening network to function as the entry point to a continuing healthcare system rather than as an isolated testing exercise.
The progress recorded so far provides a substantial base. More than seven crore people have now been screened, according to the government’s dashboard, demonstrating the reach of the national programme.
The next stage will involve ensuring that people who test positive do not disappear from the healthcare system after receiving their results.
Better tracking, counselling, medicine supplies, specialist referrals and community-level follow-up could help close that gap.
For families affected by sickle cell disease, the practical value of the programme will ultimately be measured not only by the number of people tested but by whether diagnosis leads to regular care and fewer serious complications.
Experts therefore argue that India’s sickle cell strategy now needs to move firmly from large-scale identification towards continuity of treatment, coordinated services and patient-centred follow-up.
The transition will be important for translating the country’s extensive screening effort into sustained improvements in the lives of people living with the disorder.

