


India’s Sickle Cell Programme Faces Next Challenge: Ensuring Continued Care After Screening
Experts say diagnosis must be followed by regular treatment, patient tracking, medicine access and specialist care to reduce complications from sickle cell disease.
New Delhi, September 30: India’s large scale effort to identify people living with sickle cell disease is entering a critical phase, with healthcare experts stressing that screening alone will not be enough unless diagnosis is followed by regular treatment, monitoring and sustained access to medicines.
India has screened more than seven crore people for sickle cell disease, identifying around 2.5 lakh patients and nearly 20 lakh carriers, according to discussions at a recent national roundtable on the condition. Experts said the figures demonstrate the scale of the screening exercise while also drawing attention to the challenges patients face after receiving a diagnosis.
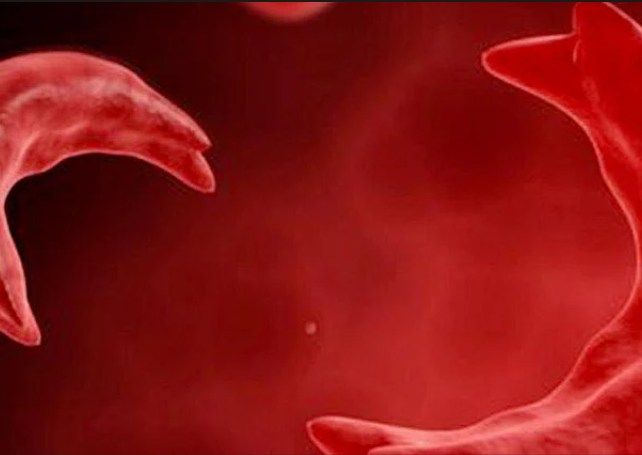
Sickle cell disease is an inherited blood disorder in which red blood cells can become rigid and take on an abnormal shape. The condition can cause anaemia, episodes of severe pain and damage to organs over time. Its impact can vary considerably between individuals, making continued medical supervision an important part of long-term care.
Healthcare stakeholders participating in the discussion said the next phase of India’s response should focus on ensuring that people identified through screening are connected to appropriate services and remain within the healthcare system.
One of the concerns raised was inadequate communication of test results. Families may undergo screening and receive a diagnosis but still face difficulties understanding what the result means, what treatment is required and where they should go for continued care.
Experts also pointed to gaps in patient tracking. Without reliable follow-up systems, individuals diagnosed through screening may not return regularly for clinical assessments or may find it difficult to access medicines close to home.
The availability of hydroxyurea was another issue highlighted during the discussions. The medicine is used in the management of sickle cell disease and can help reduce complications for appropriate patients. However, participants said shortages and difficulties obtaining regular supplies can interrupt treatment.
For families living in remote areas, distance can add another layer of difficulty. Patients may have to travel long distances simply to collect medicines or attend follow-up appointments. Such journeys can become especially challenging for people requiring regular care.
Experts suggested establishing medicine distribution points closer to communities, including village-level depots where feasible, to reduce the burden of repeated travel. Greater involvement of frontline health workers such as ASHA workers was also proposed to improve follow-up and help families remain connected with healthcare services.
Another recommendation was the creation of unique patient identification systems that could make it easier to track individuals from the point of diagnosis through subsequent stages of care. SMS-based reminders were also suggested as a practical tool for notifying patients about appointments, medicine collection and follow-up requirements.
The emphasis on continuity reflects a broader shift in the approach to sickle cell disease. Screening can identify people who may otherwise remain undiagnosed, but the health benefits of early detection depend on what happens afterward.
Patients may require regular assessment for anaemia, pain episodes and other complications. Depending on their clinical condition, some may also need specialist services or referral to centres equipped to provide advanced treatment.
Haematopoietic stem cell transplantation is one such option for selected patients. Experts at the roundtable discussed the importance of identifying suitable candidates early, noting that transplantation can have better outcomes when undertaken before irreversible organ damage occurs. Fourteen evidence-based guidelines for considering HSCT were introduced during the discussions.
Gene therapy is also being explored internationally as a potential treatment approach for sickle cell disease. However, experts stressed that foundational healthcare requirements such as infrastructure, patient identification, treatment availability and financing must continue to receive attention alongside newer technologies.
Financial assistance is another part of the challenge. While support mechanisms are available, experts said some families remain unaware of available assistance or encounter difficulties completing the required procedures. Improving awareness and simplifying access could help more eligible patients obtain support.
India has set an objective of eliminating sickle cell disease as a public-health problem by 2047. The national programme has consequently placed considerable emphasis on identifying affected individuals and carriers, particularly in communities with a higher prevalence of the disorder.
The scale of screening achieved so far represents a substantial pool of people who now require appropriate follow-up. This makes coordination between community-level workers, primary healthcare centres, district hospitals and specialised facilities increasingly important.
The use of digital tools could help build a more connected system. Patient records, automated reminders and referral tracking could allow health workers to identify individuals who miss appointments or treatment cycles and intervene earlier.
However, technology alone cannot address the practical difficulties faced by families. Medicine availability, trained personnel, laboratory services and specialist facilities remain essential components of long-term sickle cell care.
Experts have therefore called for a patient-centred approach in which screening is treated as the starting point rather than the endpoint of intervention. Such a model would require patients to receive clear information about their condition, access appropriate medicines and undergo regular monitoring.
The discussion also highlighted the importance of involving families in treatment decisions. Since sickle cell disease is inherited, identifying carriers can provide families with information that may be relevant to genetic counselling and future health decisions.
India’s progress in screening has created a significant foundation for tackling the disease, but maintaining contact with those identified through the programme will determine how effectively early detection translates into better health outcomes.
The challenge now is to build a system capable of following patients throughout their lives rather than limiting intervention to the moment a screening test produces a positive result. Strengthening medicine supply, improving communication, expanding local services and developing reliable patient-tracking mechanisms are among the measures experts say could help bridge that gap.
With millions of people already identified as patients or carriers through screening, the next stage of India’s sickle cell response will increasingly depend on the strength of follow-up services. The focus is consequently shifting from simply finding cases to ensuring that every diagnosed person can access sustained and appropriate care.

